What is colorectal cancer?
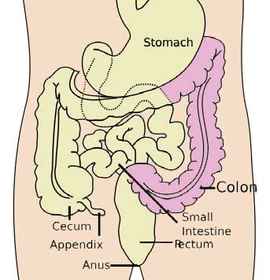
The colon, or large intestine, is made up of four layers:
- Mucosa: The innermost layer, containing glandular cells that produce mucus. Colorectal cancer typically begins in this layer.
- Submucosa: Contains blood vessels, lymphatic tissue, and connective tissue.
- Muscularis Propria: A thick muscle layer that helps move waste through the colon.
- Serosa: The outermost protective layer.
In Singapore, colorectal cancer is the most common cancer, affecting approximately 45 out of every 100,000 people.
Colorectal cancer develops when cells in the colon or rectum undergo genetic mutations that cause uncontrolled growth and division. This process often begins with the formation of polyps—non-cancerous growths on the inner lining of the colon or rectum. While not all polyps become cancerous, certain types, such as adenomatous polyps, have a higher risk of transforming into malignancies over time.
What are the signs & symptoms of colorectal cancer?
- Rectal bleeding or blood (either bright red or very dark) in the stool
- A change in bowel habits
- Persistent abdominal discomfort such as cramps or pain
- Incomplete emptying of the bowel
- Unexplained weight loss
A doctor should be consulted if the above symptoms occur.
What are the risk factors of colorectal cancer?
- Common amongst those above 50
- Family history of colon or rectum cancer
- Previous history of colon polyps
- A history of ulcerative colitis (ulcers in the lining of the large intestine) or Crohn’s disease
- Smoking
- Alcohol intake
- Diet high in fried food and red and processed meat
What can you do to prevent colorectal cancer?
- Increase fiber intake (fruits, vegetables, whole grains).
- Reduce consumption of red and processed meats.
- Limit alcohol intake and avoid smoking.
- Regular physical activity
- Maintain a healthy weight
- Control diabetes and inflammatory bowel diseases (Crohn's disease, ulcerative colitis)
What is screening for colorectal cancer?
The best way to protect yourself from colorectal cancer is through regular screenings. Colorectal cancer often develops without noticeable symptoms in its early stages, so early detection can significantly improve treatment outcomes. Regular FOBT or FIT tests help detect precancerous polyps or cancer at an early, more treatable stage.
| Age |
Fecal Occult Blood Test (FOBT) / Fecal Immunochemical Test (FIT) |
| Below 45 |
Not required for average-risk individuals |
| 45-49 |
Once a year |
| 50 and above |
Once a year |
Note: Those with a family history of colorectal cancer, inflammatory bowel disease, or genetic syndromes may need earlier and more frequent screenings.
There are various screening tests available:
- Colonoscopy: Every 10 years
- Fecal Immunochemical Test (FIT): Every year
- CT Colonography (Virtual Colonoscopy): Every 5 years
However, the Faecal Occult Blood Test (FOBT) is the only screening modality that has been shown in three large randomised trials to show a 33% reduction in colorectal cancer mortality.
How is colorectal cancer diagnosed?
To detect colorectal cancer, the following screening tests are commonly used:
- Fecal Immunochemical Test (FIT): Similar to FOBT but specifically detects human haemoglobin in stool, making it more accurate and requiring no dietary restrictions before testing.
- Physical exam: Your doctor checks your general health, including checking for signs of disease, such as lumps or anything else that seems unusual.
- Digital rectal exam: The doctor inserts a lubricated gloved fi¬nger into the rectum to feel for lumps or anything that seems unusual. However, this detects cancer only in the last 5 to 8 centimetres of the rectum.
- Colonoscopy: A more comprehensive procedure where a longer, flexible tube examines the entire colon and rectum. Polyps or suspicious tissue can be removed during the procedure for biopsy.
- CT Colonography (Virtual Colonoscopy): A non-invasive imaging test that uses CT scans to create detailed pictures of the colon, helping to identify polyps or tumours.
Importance of Early Detection:
Early detection of colorectal cancer is crucial, as it significantly increases the chances of successful treatment and survival. Regular screening can identify precancerous polyps, allowing for their removal before they develop into cancer. Studies have shown that up to 90% of colorectal cancers can be cured if found early.
What are the treatment options for colorectal cancer?
Treatment Options
Depending on the stage of the colorectal cancer, there are various treatment options available. The main types of treatment that can be used for colorectal cancer include the following.
Surgery
Surgery is the most common kind of treatment for all stages of colorectal cancer. There are various forms of surgery to remove the cancer, including:
- Local excision: If the cancer found is at an early stage, it may potentially be resectable through local excision using a colonoscope (Endoscopic Mucosal Resection / Endoscopic Submucosal Dissection) or through transanal surgery for rectal cancers.
- Resection with or without colostomy: If the cancer is larger, the doctor will perform a colectomy to remove the cancer and a small amount of healthy tissue surrounding it. The ends of the colon are then sewn back together. If the doctor is not able to sew the two ends of the colon back together, a stoma is made on the outside of the body for waste to pass through. This procedure is called a colostomy. A bag is placed around the stoma to collect the waste.
Chemotherapy
Chemotherapy is the use of drugs to stop the growth of cancer. It can be administered by injecting drugs into the vein. Depending on the stage of the cancer, chemotherapy may be required after surgery to prevent recurrence and improve a person's chance of survival. Chemotherapy may be used for patients with very advanced colorectal cancer which cannot be cured by surgery or have spread to other parts of the body.
Radiation Therapy
Radiation therapy is a cancer treatment that uses high-energy x-rays or other types of radiation to kill cancer cells or keep them from growing. Radiation therapy is usually used after surgical removal of the cancer to kill any residual cancer cells around the original tumour site. It can also be used together with chemotherapy to shrink a large colorectal cancer before surgery.
Treatment options (by stages)
[Stage 0] Precancerous or Non-Invasive Colorectal Cancer: The cancer is in the innermost layer of the colon or rectum and has not spread beyond the surface lining.
- Local Excision Surgery
- The tumour can be removed without cutting through the abdominal wall.
- A colonoscope (a thin, flexible tube) is inserted through the rectum to remove the abnormal tissue.
[Stage 1] Early-Stage Colorectal Cancer: The cancer has grown into deeper layers of the colon wall but has not spread to the lymph nodes.
- Surgery (Colectomy / Local Excision)
- If small and localised: The tumour can be removed via a colonoscopy.
- If larger: A segment of the colon may need to be surgically removed (colectomy).
[Stage 2] Localised Colorectal Cancer: The cancer has grown through the wall of the colon or rectum but has not spread to lymph nodes.
- Surgery (Colectomy with Lymph Node Removal)
- The affected section of the colon is removed along with nearby lymph nodes.
- The healthy ends of the colon are reconnected.
- Chemotherapy (Sometimes Used)
- If the tumour is large or has high-risk features, chemotherapy may be recommended to prevent recurrence.
[Stage 3] Advanced Localised Colorectal Cancer: The cancer has spread to nearby lymph nodes but not to distant organs.
- Surgery (Colectomy with Extensive Lymph Node Removal)
- The affected part of the colon and multiple lymph nodes are removed.
- In some cases, a colostomy (an opening for waste removal) may be needed.
- Chemotherapy (Standard Treatment After Surgery)
- Used to destroy any remaining cancer cells and reduce recurrence risk.
- Radiation Therapy (Especially for Rectal Cancer)
- Helps shrink tumours before surgery or kill remaining cancer cells post-surgery.
[Stage 4] Metastatic Colorectal Cancer: The cancer has spread to distant organs, such as the liver, lungs, or peritoneum.
- Surgery (Palliative or Curative in Select Cases)
- If possible, the primary tumour and metastases (such as liver or lung tumours) may be surgically removed.
- Colostomy or stent placement may be done to relieve symptoms if the tumour is blocking the bowel.
- Chemotherapy (Main Treatment for Stage 4 Cancer)
- Used to slow disease progression and improve survival.
- Targeted Therapy & Immunotherapy
- Used in certain patients with genetic markers that respond to these treatments.
- Radiation Therapy (For Symptom Relief)
- Used to shrink tumours and reduce pain or bleeding.
- Palliative Care
- Focuses on symptom management, pain control, and improving quality of life.
Surgical Options
Surgery is a primary treatment for colorectal cancer, especially in its early stages. The choice of surgical procedure depends on the tumour's location, size, and stage. Here are the main surgical options:
- Polypectomy and Local Excision: For very early-stage cancers or precancerous polyps, these can often be removed during a colonoscopy. A polypectomy involves removing the polyp, while a local excision removes the cancer and a small margin of healthy tissue.
- Colectomy: The surgeon removes the cancerous part of the colon along with a margin of healthy tissue and nearby lymph nodes. The remaining sections are then reattached if appropriate. Most surgeries are now conducted using Minimally Invasive approaches (laparoscopic and robotic). These allow for smaller incisions with quicker recovery and less pain.
- Colostomy or Ileostomy: In cases where reconnection of the bowel isn't possible immediately or ever, the surgeon creates an opening (stoma) on the abdomen's surface to allow waste to exit the body. This can be temporary or permanent, depending on the individual case.
After surgery, additional treatments such as chemotherapy or radiation therapy may be recommended to reduce the risk of recurrence, depending on the cancer's stage and other factors.
What is post-treatment for colorectal cancer?
Recovery after colorectal cancer treatment focuses on digestive health, preventing recurrence, and improving overall well-being.
1. Regular Follow-Up Care
- Screening and Surveillance: Routine colonoscopies, blood tests, and imaging help detect any recurrence early.
- Monitor Digestive Health: Report symptoms like persistent diarrhoea, constipation, or abdominal pain.
2. Digestive Health and Diet
- High-Fibre Foods: Whole grains, fruits, and vegetables aid digestion and prevent constipation.
- Hydration: Drink plenty of fluids to maintain bowel regularity.
- Avoid Heavy or Greasy Foods: Some foods may cause discomfort, especially after surgery.
3. Physical Activity and Recovery
- Light Exercise: Walking and yoga help maintain strength and prevent complications like blood clots.
- Gradual Return to Normal Activities: Increase physical activity levels based on your energy levels.
4. Emotional and Mental Health
- Support Groups and Counselling: Helps manage post-treatment anxiety and emotional stress.
- Mindfulness Practices: Meditation, breathing exercises, or journaling may help improve mental well-being.
5. Colostomy Care (If Applicable)
- Proper Stoma Care: If a colostomy was performed, learn how to manage and care for the stoma.
- Dietary Adjustments: Certain foods may affect stoma output and should be monitored.
6. Lifestyle Adjustments
- Limit Alcohol and Red Meat: Helps reduce the risk of recurrence.
- Regular Health Check-Ups: Keep up with routine medical visits and screenings.
By following these post-treatment guidelines, colorectal cancer survivors can improve their quality of life and maintain overall health.
Enhanced recovery after surgery for colorectal cancer?
The demand for surgical services is on the rise, especially with major surgeries, which pose challenges for patients. Evidence indicates that comprehensive patient management throughout the surgical journey can significantly improve outcomes and accelerate recovery.
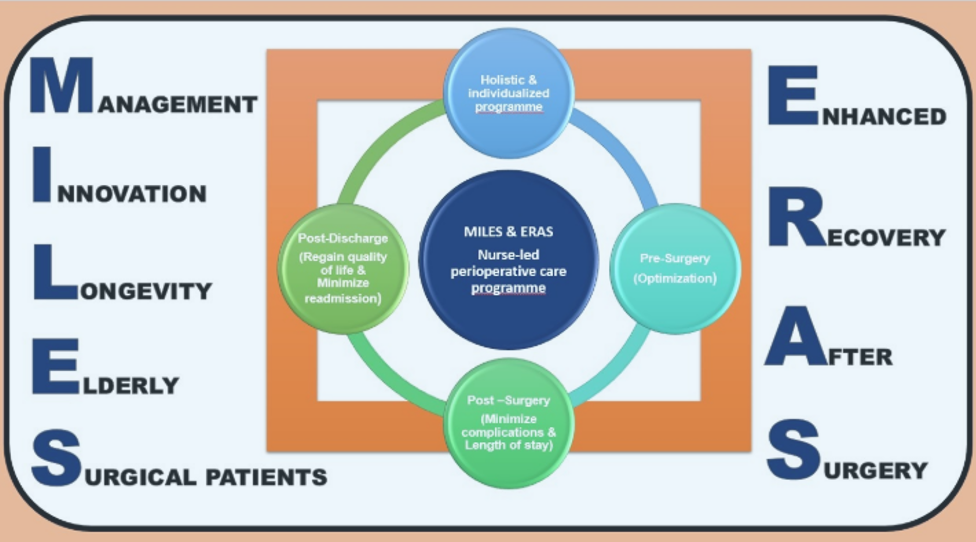
To that end, we have established two nurse-led perioperative care programmes designed for patients undergoing major surgery. These programmes are holistic and tailored to provide multidisciplinary care throughout the patient's surgical experience.
For patients aged 65 years and above, we introduce the Management and Innovation for Longevity in Elderly Surgical (MILES) programme—a nurse-led initiative that represents an advanced version of the ERAS programme. Its primary objective is to assist elderly patients in swiftly returning to their pre-surgery level of function. For patients under 65 years, we offer the Enhanced Recovery After Surgery (ERAS) programme. As anticipated, these programmes have shown excellent outcomes.
Living with colorectal cancer?
Cancer survivorship starts when a person is diagnosed with cancer and continues through the cancer journey and beyond. Once treatment is completed, in addition to looking out for long-term side effects related to treatment and regular monitoring by your healthcare team to detect recurrence, it is important that you stay well and live well!
The mission of the NCIS Personalised Wellness Programme (formerly known as NCIS Cancer Survivorship) is to provide a holistic and personalised end-to end support, that begins right from the point of diagnosis, through treatment, to survivorship and end-of-life care. We understand that every person has unique physical, psychological and social needs and our spectrum of services will help, guide and empower you and your caregivers.
To find out more, download our brochure, visit our Programmes and Activities page, or take a look at our Calendar of Events here!
We introduced our colorectal survivorship discharge programme in 2017. Working closely with our colleagues in primary care, patients who have completed their 5 year follow up journey will get discharged back under the care of polyclinics and GPs. We provide a full summary of their treatment journey, with a recommendation when to return for a follow up colonoscopy at the hospital. This programme ensures that patients are well taken care of, their condition is communicated effectively to the polyclinic doctors and GPs, and patients do not have to come back to the hospital for unnecessary tests and consultations.



























