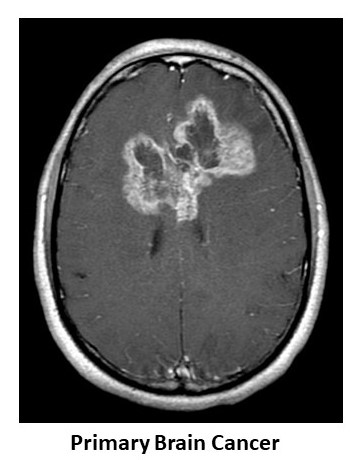
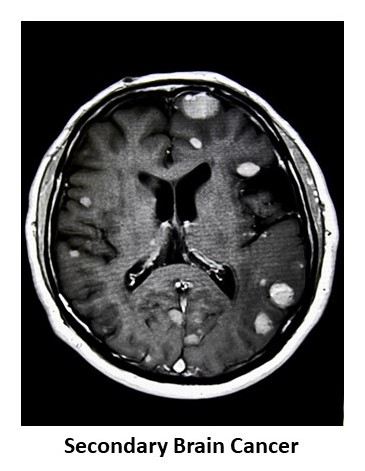
What is brain cancer?
The brain, a central component of the nervous system, comprises various cell types, including:
- Neurons: The primary signaling cells responsible for transmitting information throughout the body.
- Glial Cells: Supporting cells that provide structural and metabolic support to neurons.
Brain cancer develops when these cells undergo genetic mutations that lead to uncontrolled division and growth, forming tumours. These tumours can disrupt normal brain function by invading surrounding tissues or increasing intracranial pressure.
Brain cancers are classified into two main categories:
- Primary Brain Cancer: Originates within the brain. These cancers can arise from various cell types, including:
- Glial Cells: Tumours arising from glial cells are termed gliomas.
- Neuronal Tumours: Less commonly, tumours can develop from neurons themselves.
The World Health Organization (WHO) classifies these tumours based on their histological features and molecular characteristics, ranging from low-grade (less aggressive), Diffuse Low Grade Gliomas (DLGG), to high-grade (more aggressive) malignancies, Glioblastoma Multiforme (GBM).
- Secondary (Metastatic) Brain Cancer: Occurs when cancer cells from other parts of the body spread to the brain via the bloodstream. Common primary cancers that metastasize to the brain include lung, breast, kidney, and skin cancers. Secondary brain tumours are more prevalent than primary brain tumours.
Early detection and accurate classification of brain tumours are crucial for determining the most effective treatment strategies and improving patient outcomes.
What are the signs & symptoms of brain cancer?
In general, signs and symptoms of having a brain tumour depend very much on the type of brain tumour, the rate of growth and its anatomical location in the brain. Some symptoms are as follows:
- Headaches (persistent, especially early morning headaches)
- Nausea and vomiting
- Seizures
- Blurring of vision
- Weakness or numbness on one side of the body (very similar to stroke-like symptoms)
- Difficulty walking (gait instability)
- Problems with language and speech such as word-finding difficulty
- Memory loss
A doctor should be consulted if the above symptoms occur.
What are the risk factors of brain cancer?
- Certain gene mutations (such as oncogenes) may predispose patients to develop primary brain cancer.
- Those with a history of radiation therapy.
- Those with a known history of other cancers such as breast, lung, prostate, kidney, etc. (brain metastasis).
What can you do to prevent brain cancer?
While there are no guaranteed ways to prevent brain cancer, lifestyle changes that may reduce risk include:
- Limiting exposure to radiation (e.g., unnecessary CT scans, occupational hazards).
- Avoiding exposure to carcinogenic chemicals.
- Maintaining a healthy lifestyle (balanced diet, regular exercise).
- Managing chronic conditions such as high blood pressure and diabetes.
- Understanding genetic predispositions and seeking medical advice if there is a family history.
Compliance with treatment of other cancers can potentially prevent secondary brain cancer.
How is brain cancer diagnosed?
Patients suspected of having a brain tumour or cancer will be referred to a neurosurgeon for a detailed neurological assessment, followed by imaging studies.
- Neurological examination: A comprehensive assessment conducted by a neurologist or neurosurgeon to evaluate cognitive function, coordination, reflexes, vision, and other neurological aspects.
- Magnetic Resonance Imaging (MRI): Utilises magnetic fields and radio waves to produce detailed images of the brain, aiding in the detection of tumours and assessment of their extent.
- Computed Tomography (CT) Scan: Employs X-rays to create cross-sectional images of the brain, useful in certain scenarios where MRI is contraindicated.
Importance of early detection in brain cancer
>Detecting brain cancer early allows for timely intervention, increasing the chances of successful treatment and improving survival rates. Early diagnosis can help prevent tumour progression, reduce complications, and provide more treatment options, including less aggressive therapies. Since brain tumours can affect critical functions, early detection also helps preserve neurological function and quality of life.
|
What are the treatment options for brain cancer?
The treatment of brain cancer depends on the type of brain cancer.
Primary brain cancer
Treatment generally consists of a combination of brain surgery followed by adjuvant therapy such as chemotherapy and radiotherapy. For Diffuse Low Grade Gliomas (DLGG), early and maximal surgical resection is currently the first line of treatment.
Secondary brain cancer
Treatment will very much depend on the type of primary cancer and the extent of systemic disease. Treatments of brain metastasis may include brain surgery, gamma knife radiosurgery, radiotherapy, or chemotherapy.
Brain mapping surgery (Awake or Asleep)
Brain Mapping Surgery is a treatment option for removal of tumours near the brain regions that control vital body functions, or sensory and language capabilities. Some brain tumours are found in areas of the brain that control speech, language, or motor control of the arms and legs. These tumours can be both primary or secondary brain tumours.
Brain mapping surgeries allow brain tumours to be removed while preserving important functions such as language, fine motor skills, and executive functions. For infiltrative tumours, brain mapping surgery allows for maximal surgical resection of the tumour whilst preserving patients' neurological functions, and is now the standard practice.
Contrary to common belief, patients tolerate the awake procedure well. The brain cannot feel pain. During surgery, functions such as speech, language, and movement can be tested and patients can provide real-time feedback to the neurosurgeon as the tumour is being excised. This allows the neurosurgeon to safely remove more of the tumour whilst preserving the patient's functions.
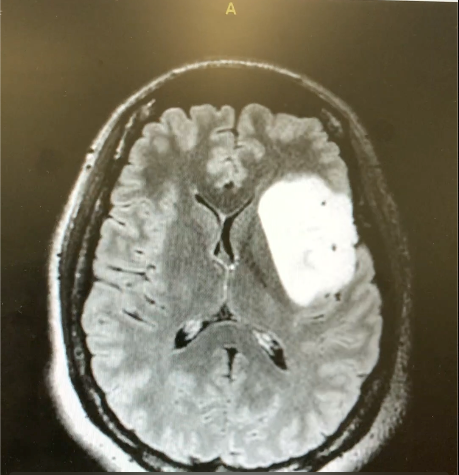
MRI image of a left insular diffuse low grade glioma
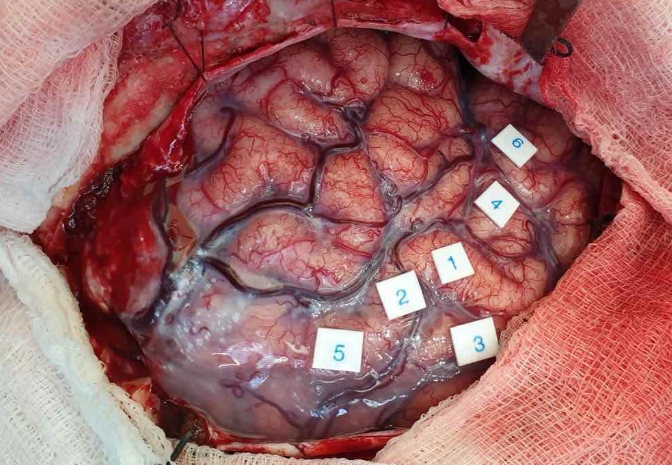
Intraoperative photo of brain mapping (labels indicate eloquent areas of the brain)
Treatment options (by stages)
[Stage 0] Precancerous or non-Invasive brain tumours
The tumour is in an extremely early stage, often discovered incidentally on imaging scans. It has not spread or caused symptoms yet.
Active surveillance
- No immediate treatment is required.
- Regular MRI or CT scans are scheduled to monitor for growth or changes.
Surgery (if necessary)
- If the tumour shows signs of growth or is in a critical brain area, early surgical removal may be considered to prevent complications.
[Stage 1] Early-stage brain cancer
The tumour is slow-growing and has not spread to nearby brain tissue.
Surgery
- The primary treatment is surgical removal of the tumour. If the tumour is in an accessible location, complete resection may be curative.
- Some small, asymptomatic tumours may be monitored with regular scans instead of immediate surgery.
Observation
- If the tumour is not causing symptoms, doctors may choose active surveillance with periodic MRI scans.
[Stage 2] Localised brain cancer
The tumour grows slowly but may start to invade surrounding brain tissue.
Surgery
- Maximal safe resection is performed to remove as much of the tumour as possible while preserving brain function.
- If the tumour is in a critical brain area, awake brain surgery (brain mapping) may be used to avoid damage to essential functions like speech and movement.
Radiation therapy
- Used if some tumour remains after surgery or if the tumour has an increased risk of progression.
- Helps target any cancer cells left behind.
Chemotherapy
- May be recommended for certain tumour types that are more aggressive.
- Can be used if complete surgical removal is not possible.
[Stage 3] Advanced brain cancer
The tumour is growing more quickly and may have spread into nearby areas of the brain.
Surgery
- Aggressive tumour removal is performed if possible. However, due to the tumour's invasive nature, complete resection may not always be achievable.
Radiation therapy
- Almost always recommended after surgery to destroy remaining cancer cells.
Chemotherapy
- Often used in combination with radiation therapy to slow tumour growth and reduce recurrence.
- Common drugs include Temozolomide (TMZ).
Targeted therapy (if applicable)
- Some brain tumours have specific genetic mutations that can be targeted with newer drugs.
Steroid therapy
- Used to reduce swelling and relieve pressure on the brain.
[Stage 4] Metastatic or late-stage brain cancer
The tumour is highly aggressive, grows rapidly, and may have spread within the brain or to the spinal cord.
Surgery
- Not always an option, especially if the tumour is widespread. However, palliative surgery may be done to relieve pressure on the brain and improve symptoms.
Radiation therapy
- Used to slow cancer progression and control symptoms.
- Whole brain radiation therapy (WBRT) may be used if multiple brain metastases are present.
Chemotherapy
- Helps manage the disease, but at this stage, it is typically not curative.
Targeted therapy and immunotherapy
- Some tumours may respond to newer targeted drugs or immunotherapy, depending on the genetic profile of the cancer.
Palliative care
- Focuses on symptom relief and improving quality of life.
- Includes pain management, seizure control, and psychological support.
Surgical options
Surgery is one of the primary treatments for brain cancer, particularly for tumours that are accessible and can be safely removed. The type of surgery depends on the location, size, and type of tumour. Here are the main surgical options:
- Craniotomy: The most common brain surgery for tumour removal. A section of the skull is temporarily removed to access the tumour, and then replaced after surgery. This can be performed under general anaesthesia or as an awake craniotomy for tumours near critical brain areas.
- Awake brain surgery (brain mapping craniotomy): Performed while the patient is awake to preserve functions such as speech and motor control. Commonly used for tumours near critical brain areas.
- Stereotactic brain surgery: Used when the tumour is in a deep or hard-to-reach area of the brain. A small hole is drilled into the skull, and a needle is used to extract a tissue sample for diagnosis.
- Endoscopic brain surgery: A minimally invasive procedure where a small tube with a camera (endoscope) is inserted through a small opening in the skull or through the nasal cavity to remove the tumour.
- Laser interstitial thermal therapy (LITT): A minimally invasive procedure where a laser heats and destroys tumour cells. It is guided by MRI and is suitable for deep-seated or inoperable tumours.
- Shunt placement: If the tumour causes a buildup of cerebrospinal fluid (hydrocephalus), a shunt is inserted to drain excess fluid and relieve pressure.
- Transsphenoidal surgery (For pituitary tumours): A specialised approach to remove tumours in the pituitary gland through the nasal cavity, avoiding the need for a skull incision.
- Debulking surgery: If complete removal of the tumour is not possible, part of the tumour is removed to reduce pressure on the brain and improve symptoms.
After surgery, additional treatments such as radiation therapy, chemotherapy, or targeted therapy may be required to prevent recurrence and control remaining tumour cells.
What is post-treatment for brain cancer?
Recovering from brain cancer treatment can take time, and managing side effects is essential for improving quality of life.
Follow-up care & monitoring
- Regular follow-up appointments with your oncologist and neurologist to monitor for recurrence or complications.
- MRI or CT scans as recommended to check for any tumour regrowth.
- Report any new or worsening symptoms, such as headaches, seizures, or cognitive changes.
Rehabilitation & therapy
- Physical therapy: Helps regain strength, coordination, and mobility.
- Occupational therapy: Assists with daily activities and fine motor skills.
- Speech therapy: If speech or swallowing was affected, therapy can improve communication and eating abilities.
- Cognitive therapy: Helps with memory, concentration, and problem-solving skills.
Medication management
- Continue prescribed medications, such as anti-seizure drugs or steroids, to manage inflammation and prevent complications.
- Monitor and report any side effects of medications.
Lifestyle & nutrition
- Healthy Diet: Eat a balanced diet rich in protein, fruits, and vegetables to support recovery.
- Hydration: Drink enough water to avoid dehydration and fatigue.
- Exercise: Engage in light physical activity as recommended by your doctor to regain strength and energy.
- Adequate Rest: Ensure proper sleep to help the body heal and manage fatigue.
Emotional & mental well-being
- Counselling or Support Groups: Joining a cancer support group or seeing a therapist can help with emotional recovery.
- Mindfulness & Stress Management: Techniques such as meditation, deep breathing, or yoga may help with anxiety and mental clarity.
Preventing recurrence & managing iong-term effects
- Avoid smoking, alcohol, and exposure to harmful chemicals.
- Engage in activities that stimulate the brain, such as reading, puzzles, or learning new skills.
- Discuss long-term effects with your doctor and plan for adjustments in daily life if necessary.
Return to work & daily activities
- Gradually ease back into work or daily responsibilities based on your energy levels and your doctor's advice.
- Consider occupational therapy or workplace accommodations if needed.
Post-treatment recovery is different for every patient. Following a personalised care plan and maintaining a healthy lifestyle can help improve long-term well-being.
Information on brain mapping
In the brain mapping procedure, functions such as speech, language, and movement can be tested and patients can provide real-time feedback to the neurosurgeon as the tumour is being excised. This allows the neurosurgeon to safely remove more of the tumour whilst preserving the patient's functions.
Prior to the surgery, the patient will be reviewed by a team of specialists involved in the brain mapping surgery, namely the neurosurgeon, neuroanaesthetist, and neuropsychologist.
The neuroanaesthetist will discuss with the patient about any past medical problems and examine the patient. The whole process of sedation required during the more uncomfortable phases of the surgery — including the drilling of the skull and insertion of intravenous cannulae and urine catheter — will also be explained. The patient might experience some headaches and muscle pain from lying in the same position for several hours.